

Despite all struggles, Germany remains the biggest healthcare system in Europe, with roughly €500 billion in annual volume. So anyone interested in building a large healthtech startup in Europe usually has the German market on their map.
Right now, the system is under reform, and it’s far from over. The current reform wave started with 66 recommendations from an expert commission, the Finanzkommission Gesundheit. I wrote about it earlier this year. The question back then was: what do politicians make out of it? Tbh, we kind of knew we wouldn’t like the answer... but now we know more.
The resulting law (the “BStabG” -> peak German abbreviation) has sparked debates ranging from nerdy and interesting to outright ridiculous. I’ll pick up three of my favourite debates to add context and predict their impact on startups.
1. Budgeting everything
One of the first answers to the cost-cutting question in the German statutory system is always strict budgeting. Unsurprisingly, it’s what they did here and will continue to do. Essentially, they’re placing a brutal cap on all spending, tied to the system’s income: no sector may grow faster than contribution income, minus an extra percentage point from 2027 to 2029.

In the current form of the law, two groups are hit the hardest:
Hospitals. They carry the largest single chunk, worth billions. Wage increases above the cap won’t be fully refinanced, and the nursing budget loses its full-cost-cover status. The hospital association claims half of all sites will be insolvency-threatened by 2030. That’s for sure biased, but the direction seems right.
Primary care physicians. Across specialties in outpatient clinics, add-on payments worth over €2.5 billion get cut (fast-track appointment bonuses, personal health record onboarding fees, and more), and some of the reimbursement caps previously lifted are now reinstalled. The Zi (a research institute) calculated an average revenue loss of ~€24k per practice, up to €68k per doctor in some specialties! GPs usually have the slimmest margins, so they’re hit the hardest. For many it’s the difference between being profitable or not.
Background for the non-Germans: Even before the reform, it’s no secret that many clinics operate at a loss if you just consider the statutory insurance patients. The manager of a large outpatient center told me: “I lose money on every single statutory patient. It barely covers my overhead costs”. These clinics are cross-financed from private insurance patients. On average, German outaptient clinics have 10% private patients who contribute 30%+ of the revenue. The reform will likely widen that gap.
An interesting side debate evolved around the so-called HZV (Hausarztzentrierte Versorgung). It’s the primary-care-first model where patients voluntarily enroll and commit to using their GP as the contact point and gate to specialists. Remember that Germans are not used to this! Traditionally they had the freedom to walk straight into any specialist’s office. The HZV is an attempt to slowly change this by giving GPs extra reimbursement per enrolled patient. That reimbursement is formalized via direct contracts with the insurers. It was supposed to be an incentive, and GPs liked the extra cash.
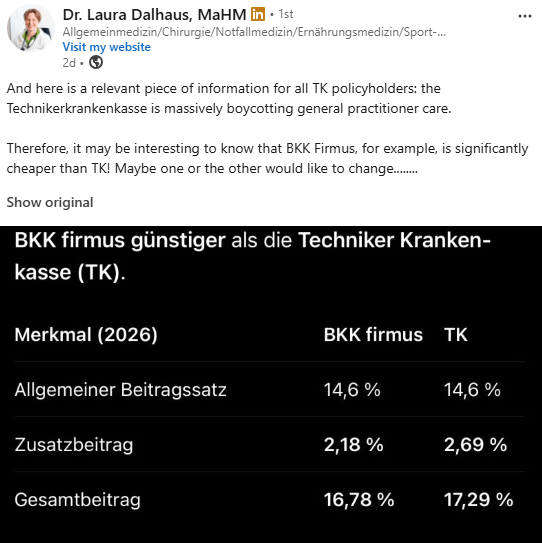
Now Techniker Krankenkasse, Germany’s biggest insurer with 11m patients, published an evaluation saying HZV neither avoids specialist contacts nor hospital stays while costing them €160 million a year extra, and promptly canceled its HZV contracts. Massive outrage among GPs followed online, and the GP association calls it a “campaign against the GPs”. Some doctors even publicly recommended their patients to switch insurers. What a time to be alive, where physicians start online shit storms!
For startups, all of this boils down to one thing: It’s even more important to prove your ROI. All “nice to have” products will be cut from clinic P&Ls. If you’re helping GP clinics or hospitals save money or increase liquidity, this is going to be a boost for you.
And if you run a GP clinic yourself, it means running even tighter processes and being even smarter about where to focus your resources.
2. Let the patients do more
Two points hit patients directly - and because they do, they sparked massive public backlash.
The first is increasing co-pays. They rise from €5-10 today to €7.50-15, and get indexed to wage growth going forward. Symbolically important but, in absolute terms, negligible. 72% of Germans reject the increase (wow, surprise!), but I’m with the legislators here. Think about it:
Co-pays haven’t moved since 2004 while wages grew roughly 50%. The patients got off lightly, in my opinion. It’s a very fair adjustment
The annual out-of-pocket cap stays untouched anyways
US patients would frantically laugh about this. €15 co-pay? What is this, healthcare for ants?

I honestly believe patients need to share parts of the responsibility for healthcare costs, and a small participation like this supports that

The second change is the one that dominated German social media this week. It wasn’t in the law itself, but the coalition committee decided it on Wednesday on top of everything else.
What happened? Today, Germans only need a sick note from the fourth day of illness onwards. In the first days, you just call in sick, no questions asked. The government now plans to enforce official sick notes immediately from day one. That alone would perhaps be fine, but on top they want to prohibit phone-based sick notes. Which means for every single flu or fever you’d need to walk to your local doctor?!
If that passes, it’s an incredibly useless and burdensome measure. Yes, Germany tops the OECD in recorded sick days, roughly 20 per employee per year. But is this the correct counter-measure? It likely hits the wrong people and burdens the system:
The demand for sick notes would multiply, flooding primary care clinics that are over capacity already. The doctor’s association called the plan an “imposition bordering on insolence”
Besides being super annoying for patients, it’s questionable whether it even has an effect on sickness rates. Online, many commented that if they’re forced to see a doctor, they’d also get a longer sick note
One caveat here: Sick notes via video consultation seem to remain possible, although there are limits. It’s allowed to write notes for up to 7 days for known patients, and up to 3 days for unkown patients. It would buffer the demand shock, so I can’t fully buy into the public panic - unless they also prohibit video consultations. That would be catastrophic.
What does it mean for startups? If sick notes via video calls remain intact, telemedicine providers win massively. Besides that specific topic, I would generally prepare for a more patient-focused system, with patient opinion mattering more than it previously did. More financial responsibility = louder voice.
3. The Pharma vs DiGA debate
This topic has been more silent, probably because the affected group isn’t that large yet. I’m talking about forced price cuts in the form of rebates, initially targeted at both pharma companies and DiGA startups (digital therapeutics).
Working with rebates has been a common theme for Germany’s policymakers. The argument is volume: the more you sell, the more you should be willing to discount. While this law was discussed between lobbyists and lawmakers, something predictable happened:
Originally, the expert commission recommended doubling the manufacturer rebate on patented drugs from 7% to 14%. By the time the cabinet draft landed, that had shrunk to the existing 7% plus a temporary 3.5 points, and perhaps a “dynamic” extra rebate. Pharma now ends up contributing roughly €1.9 billion in savings of a €16 billion package. Seems like an inproportionate outcome, given that drugs are the system’s second-largest cost block with €58.5 billion in 2025 (16.6% of total GKV spending). Apparently, the standard pharma threat of moving production elsewhere does work after all. Politicians hate this trick.
DiGA, however, are still facing mandatory volume rebates of up to 30% (!) from volumes over 100k. That’s odd when you zoom out. The GKV spent €58 billion on drugs in 2025. It spent roughly €400 million on DiGA cumulatively since their launch in 2020. The entire five-year DiGA experiment cost less than 1% of a single year’s drug budget.

The rebate push comes mostly from the statutory insurers, who have hated spending money on DiGA since the beginning. It’s “just a digital product” and they doubt the efficacy claims. I find that a bit hypocritical, given that some well-reimbursed medications (e.g. antidepressants) aren’t super effective either. Another common argument is that scaling a DiGA has near-zero marginal costs because it’s just software. These people have clearly never tried marketing, selling or servicing a software product, especially not in healthcare. Sales is 80% of the game!
What does it mean for startups? The one big target of this rebate would obviously be Oviva, by far the biggest DiGA vendor and the only one anywhere near the volumes where the 30% tier applies. In general, it’s another signal to founders that purely digital therapies are not wanted at scale in the German system, and that you better find more scalable approaches to bring innovation to market. Sorry - that’s the truth.
The bottom line
Our parliament probably decides on July 10 if the law passes and whether any changes are made.
Physicians, hospital carriers and digital therapeutics are the current losers of this reform. And even if some details get walked back, the bottom line will remain: for startups, the times of loose spending in German healthcare are over. You better move closer to the revenue cycle and prove your ROI.
On a positive note - with every disruption comes opportunity. Here’s my spontaneous list of niche business ideas if the legislation passes:
digital insolvency manager for German clinics
fully managed pop-up triage tents in front of primary care clinics
mobile primary care buses handing out sick notes
end-to-end relocation services for frustrated German doctors
a service that creates almost identical DiGA twins to circumvent the 30% rebate threshold
You’re welcome to pick these up.
Speak soon,
Lucas
P.S. The law’s official name is Gesetz zur Stabilisierung der Beitragssätze in der gesetzlichen Krankenversicherung. Germany’s efficiency problem really does start with naming stuff